
-
Where does it hurt?
Common conditions
Treatments
- Fees
- Corporate DSE
- Programs
- Shop
- Contact
Mappin House, 4 Winsley St, London W1W 8HF
Mappin House, 4 Winsley St, London W1W 8HF
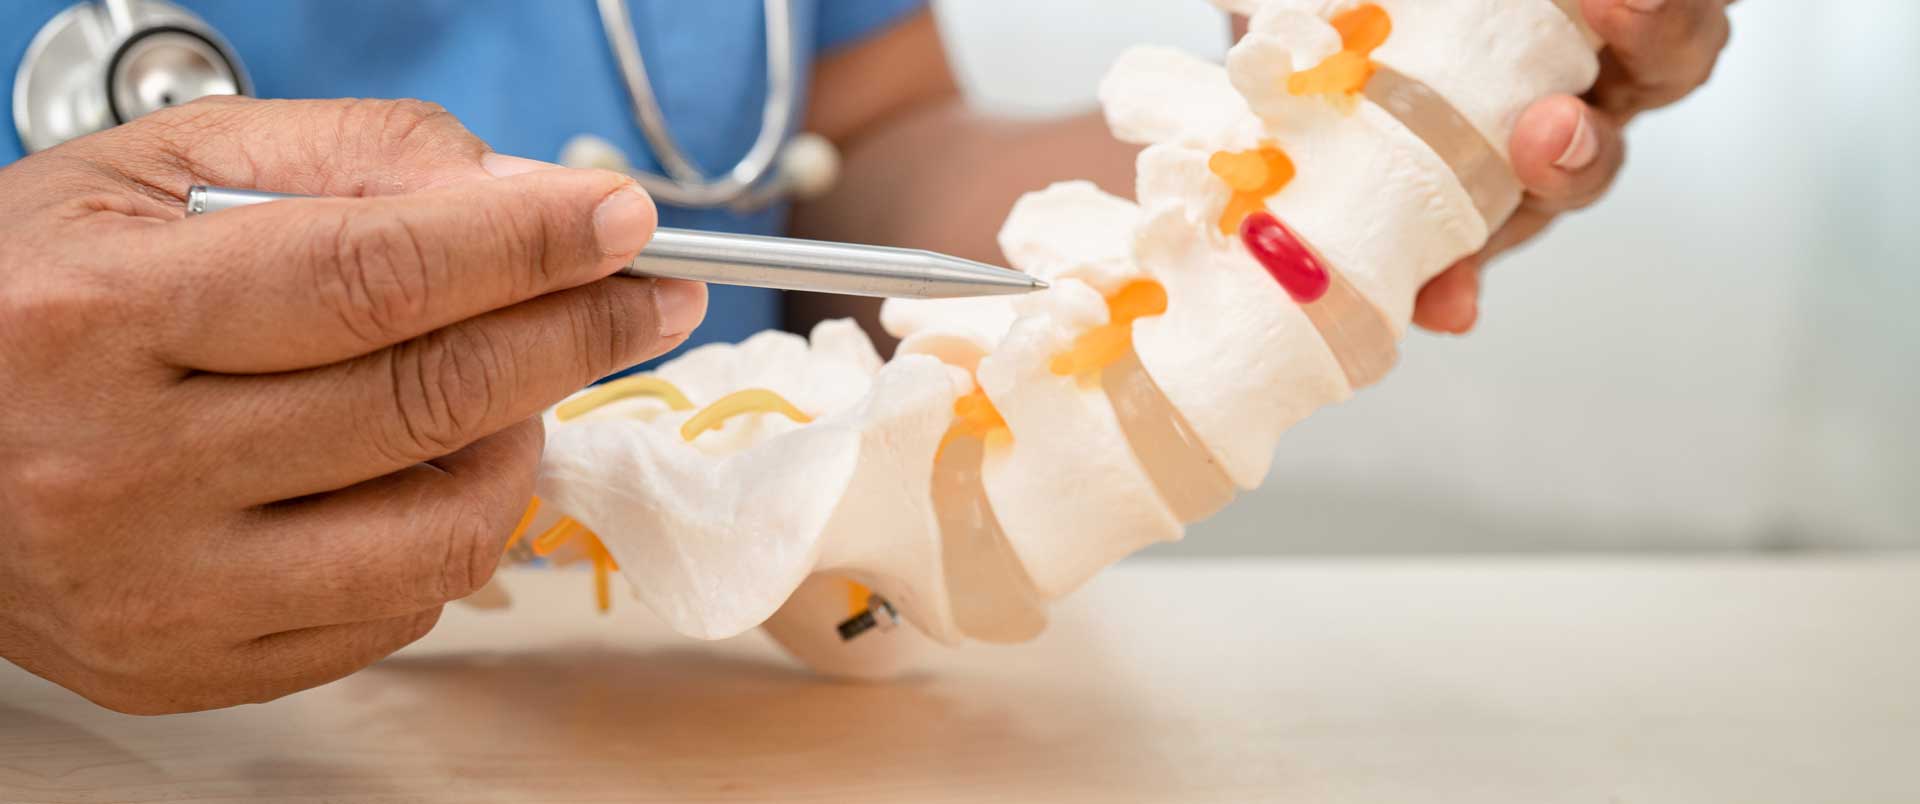
The short answer: the most common signs of a slipped disc are lower back pain, pain that shoots down one leg, and numbness, tingling or weakness in the leg or foot. Get urgent medical help for numbness around the groin or loss of bladder or bowel control.
A slipped disc, also known medically as a herniated or prolapsed disc, occurs when the soft inner nucleus of the intervertebral disc bulges or leaks through its tough outer layer. Consequently, this can press on nearby nerves, leading to pain and neurological symptoms. Although many people experience back pain at some point, recognising the signs of a slipped disc early can significantly improve outcomes and reduce the risk of chronic issues (NHS).
Intervertebral discs act as shock absorbers between the vertebrae. Firstly, each disc comprises a tough outer ring, the annulus fibrosus, and a soft, jelly-like centre, the nucleus pulposus. When the annulus weakens, due to age-related degeneration, sudden strain or repetitive loading, the nucleus can bulge or herniate into the spinal canal. As a result, nearby nerve roots may become irritated or compressed, giving rise to symptoms such as sciatica, numbness, or muscle weakness (NHS). In the lumbar region alone, around half of adults will experience back pain at some point, although not all will develop actual slipped discs (NHS Gloucestershire).
Recognising early indicators of a slipped disc can prompt you to seek professional assessment and appropriate care. Below are the most frequently reported signs of a slipped disc:
Firstly, persistent lower back pain, often dull or sharp, is the hallmark of a lumbar slipped disc. This pain may worsen with sitting, bending, or lifting and usually improves when you lie down flat.
Moreover, if the herniation irritates the sciatic nerve, you may experience sharp, shooting pain radiating from your buttock down the back of one leg.
In addition to pain, you might notice pins and needles or loss of sensation in your legs, feet or toes. These sensory changes arise when the bulging disc exerts pressure on sensory nerve fibres.
Consequently, compression of motor nerve roots can lead to weakness in the muscles supplied by those nerves. For example, you may struggle to lift your foot (foot drop) or have difficulty gripping objects if a cervical disc is involved.
Pain that intensifies during coughing, sneezing or straining (Valsalva manoeuvre) is another red flag. These actions increase intradiscal pressure, worsening nerve irritation (NHS).
However, seek urgent medical attention if you experience any of the following “red-flag” signs:
It is advisable to consult a healthcare professional if:
Your GP can often diagnose a slipped disc through a combination of history-taking and a physical examination, including leg-raise tests and neurological screening. Imaging (MRI or CT) is reserved for cases where surgery is being considered or “red-flag” conditions are suspected (NHS). Moreover, NHS and NICE guidelines recommend against routine imaging in primary care unless it will alter management (NICE).
Physiotherapists are allied health professionals specialising in musculoskeletal conditions. They play a central role in the conservative management of slipped discs by:
Indeed, NICE guidelines recommend manual therapy, such as mobilisation or massage, only alongside exercise and, if needed, psychological approaches to manage low back pain and sciatica (NICE). Consequently, timely physiotherapy input can expedite recovery and help prevent recurrence.
Regulated by the General Osteopathic Council (GOsC) since 1993, osteopaths offer manual therapy techniques, including articulation, manipulation and soft-tissue work, tailored to individual needs. Osteopaths commonly treat general, acute and chronic backache, and should hold evidence to support their interventions.
If you think you may have a slipped disc, read about how an osteopath treats a slipped disc, or book an appointment online.

Before or alongside professional care, the following strategies can help ease slipped disc symptoms:
While non-drug approaches are first-line, medications can support symptom control:
Surgery (e.g., microdiscectomy) is rarely needed and is typically reserved for patients with:
Evidence shows that most patients improve within 4–6 weeks of conservative treatment; long-term outcomes are similar whether managed surgically or non-surgically (American Academy of Family Physicians).
To minimise the risk of recurring slipped discs:
Early recognition of the signs of a slipped disc, such as radiating leg pain, numbness, or muscle weakness, is crucial. Moreover, adherence to NICE guidelines ensures safe, evidence-based care that emphasises exercise, manual therapy as part of a broader package, and judicious use of medications. By combining self-management with expert-led interventions, you can effectively manage symptoms and reduce the likelihood of future episodes.